What Is Clubfoot?
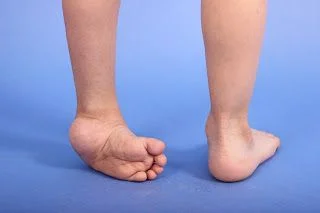
Clubfoot, medically known as Congenital Talipes
Equinovarus (CTEV), is a congenital foot deformity in which one or both
feet are positioned inward and downward at birth.
The affected foot may appear smaller and shorter than the
other foot, with the heel elevated and the arch of the foot more pronounced
than usual. The severity can range from a flexible deformity to a more rigid
and stiff foot.
When left untreated, clubfoot can affect weight-bearing and
the development of a functional walking pattern.
The Main Types of Clubfoot
Clubfoot can be classified according to its underlying cause
and associated conditions:
- 1.Idiopathic Clubfoot: The most common type, occurring in otherwise healthy infants without an identifiable cause.
- 2.Neurogenic Clubfoot: Associated with conditions affecting the nervous system, such as spina bifida or cerebral palsy.
- 3.Syndromic
Clubfoot: Occurs as part of a broader genetic, neurological, or
skeletal condition, such as arthrogryposis.
- 4.Positional
Clubfoot: Related to the baby's position inside the uterus and is
usually more flexible, without significant underlying bone deformity.
Signs and Symptoms:
A child with clubfoot may present with:
- 1.Inward
and downward positioning: The front of the foot turns inward and
downward toward the opposite leg.
- 2.High
arch (Cavus): The arch of the foot is higher and more pronounced than
normal.
- 3.Deep
skin creases: Particularly on the sole or inner side of the foot.
- 4.Smaller
foot and calf: The affected foot and calf muscles may be slightly
smaller than the opposite side.
- 5.Stiffness:
The foot and ankle may resist manual correction toward a more typical
position.
Causes and Risk Factors:
The exact cause of idiopathic clubfoot is not completely
understood. It is thought to involve a combination of genetic and biological
factors.
Factors associated with an increased likelihood of clubfoot
include:
- A
family history of clubfoot.
- Male
sex, as clubfoot occurs more frequently in boys than girls.
- Certain
factors during pregnancy, including maternal smoking.
- Neurological,
muscular, or skeletal conditions associated with non-idiopathic clubfoot.
Diagnosis and Early Intervention:
Some cases of clubfoot can be identified during pregnancy
through fetal ultrasound. However, diagnosis is most commonly made after birth
through a clinical examination.
Early treatment is important to achieve optimal
correction and support the child's development of standing and walking skills.
Treatment and the Ponseti Method
The Ponseti Method is the most widely used
conservative treatment for idiopathic clubfoot. It generally involves the
following stages:
1. Serial Casting
The foot is gently manipulated toward the corrected
position, followed by the application of a long-leg cast, which is usually
changed weekly.
Treatment typically continues for several weeks, depending
on the severity of the deformity and the child's response to correction.
2. Achilles Tenotomy
Some children require a minor procedure to lengthen the
Achilles tendon when limited ankle dorsiflexion remains after the initial
correction.
The procedure is determined by the orthopedic specialist and
is usually followed by a final period of casting.
3. Bracing
Once correction has been achieved, a Foot Abduction Brace
(FAB) is used to maintain the corrected position and reduce the risk of
recurrence as the child grows.
Consistent adherence to the bracing program is an important
part of long-term treatment success.
The Role of Physical Therapy:
Physical therapy provides supportive rehabilitation during
and after correction, with the goal of optimizing foot function and supporting
the child's overall motor development.
Depending on the child's needs, therapy may include:
Flexibility and Mobility
Gentle stretching and mobility exercises to maintain the
available range of motion and the alignment achieved after correction.
Muscle Activation
Functional activities that encourage appropriate use of the
lower-leg and ankle muscles and improve motor control.
Weight-Bearing Training
Progressive activities to develop standing and
weight-bearing while maintaining appropriate foot and ankle alignment.
Balance and Gait Training
Age-appropriate activities to improve balance, weight
shifting, motor control, and functional walking skills.
Post-Correction Follow-Up
Monitoring range of motion, strength, weight-bearing, and gait, while identifying any changes that may suggest recurrence in coordination with the orthopedic team.
The Bracing Phase: Maintaining Correction
A Foot Abduction Brace (FAB) is commonly used after
correction. It consists of two shoes connected by a bar that maintains the feet
in the prescribed position.
The orthopedic specialist determines the duration of brace
use, foot position, and daily schedule according to the child's age, condition,
and response to treatment.
For idiopathic clubfoot, adherence to the bracing program is
particularly important because early discontinuation or inconsistent use may
increase the risk of recurrence.
Home Care and When to Contact the Medical Team:
Parents can help maintain treatment results by following the
orthopedic and therapy recommendations and regularly checking the child's feet
and brace.
Parents should:
- Ensure
that the heel is properly positioned inside the shoe.
- Check
the skin regularly for persistent redness or areas of pressure.
- Follow
the prescribed bracing schedule.
- Perform
recommended home exercises correctly.
- Contact
the medical team if the heel begins to lift, the foot becomes increasingly
stiff, or the foot starts turning inward again.
Early identification of recurrence is important. In
some cases, recurrence can be managed with a period of repeat casting rather
than requiring additional surgery.
What Should Parents Expect?
Clubfoot is highly treatable, particularly when treatment
begins early and the recommended program is followed consistently.
Successful treatment does not end when the foot is initially
corrected. Continued bracing and regular follow-up are important throughout the
child's growth.
The goal is to maintain correction, support weight-bearing and motor development, and help the child achieve functional and comfortable walking
Clubfoot Care at The One Physical Therapy Center:
At The One Physical Therapy Center, we work as part
of a multidisciplinary team to support children throughout their treatment and
rehabilitation journey.
We assess mobility, flexibility, strength, weight-bearing,
balance, and gait, and develop an individualized therapy program based on the
child's age, stage of treatment, and functional needs.
Physical therapy is provided in coordination with the
orthopedic specialist, particularly during the casting and bracing phases, to
ensure that rehabilitation goals remain consistent with the correction plan.
Our goal is not only to support foot correction, but also to
help the child use the foot effectively during standing, walking, and everyday
activities.
References:
- Balasankar,
G., Luximon, A., & Al-Jumaily, A. (2016). Current conservative
management and classification of club foot: A review. Journal of
Pediatric Rehabilitation Medicine, 9(4), 257–264.
- De
Mulder, T., Prinsen, S., & Van Campenhout, A. (2018). Treatment of
non-idiopathic clubfeet with the Ponseti method: A systematic review. Journal
of Children's Orthopaedics, 12(6), 575–581.
- Morcuende,
J. A., Dolan, L. A., Dietz, F. R., & Ponseti, I. V. (2004). Radical
reduction in the rate of extensive corrective surgery for clubfoot using
the Ponseti method. Pediatrics, 113(2), 376–380.
- Rosselli,
P., Nossa, S., Huérfano, E., Betancur, G., Guzmán, Y., Castellanos, C.,
& Morcuende, J. (2015). Prenatal ultrasound diagnosis of congenital
talipes equinovarus in Bogota (Colombia) between 2003 and 2012. Iowa
Orthopaedic Journal, 35, 156–159.
- Dobbs,
M. B., & Gurnett, C. A. (2009). Update on clubfoot: Etiology and
treatment. Current Opinion in Rheumatology, 21(1), 69–72.
- Zionts,
L. E., Dietz, F. R., & Morcuende, J. A. (2012). Bracing in the
treatment of idiopathic clubfoot. Journal of the American Academy of
Orthopaedic Surgeons, 20(10), 639–647.
- van
der Ven, C. A. M., et al. (2023). Factors associated with relapse in
children with clubfoot treated using the Ponseti method. International
Journal of Environmental Research and Public Health, 20(14), 6396.